
Medical Disclaimer
This article is for informational purposes only and does not substitute professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider before making any health-related decisions.
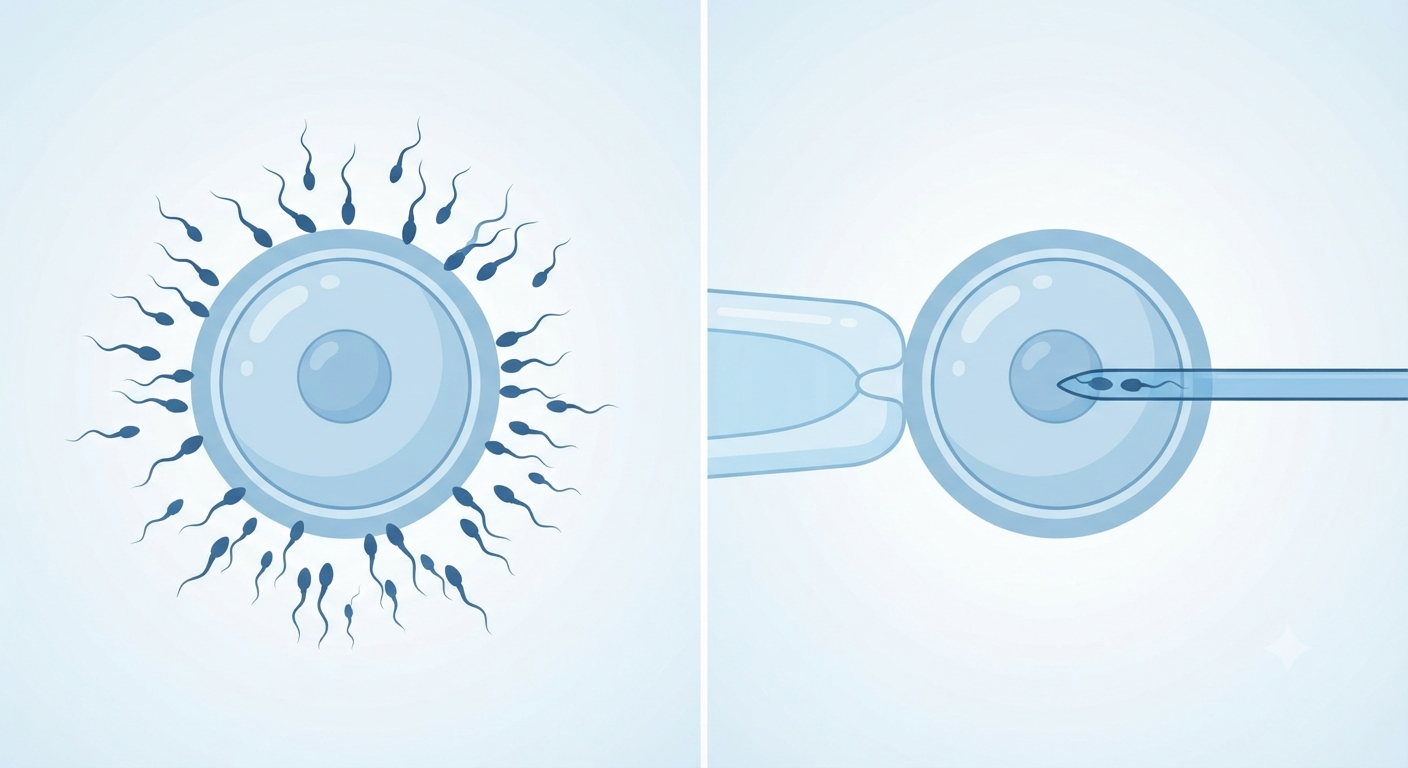
IVF vs ICSI: Why We Use ICSI for All Patients — and the Male Partner's Role
75–80%
ICSI fertilisation per mature egg
0+
ICSI cycles done at BFI
0%
Of the baby is the male partner
74 days
Time the body takes to build sperm
We've moved past conventional IVF — ICSI gives more predictable results.
Fertilisation method
ICSI for every cycle
Embryologist experience
10+ yrs, 5000+ cycles
Sperm selection
IMSI + MACS
Male-factor unit
In-house
Best suited for: Couples who want fertilisation to be one less variable — with an ICSI-only lab, advanced sperm selection, and an in-house male-infertility unit that corrects sperm issues before the cycle.
When couples ask us, "Do we need IVF or ICSI?", our answer at Bavishi Fertility Institute is clear: once we decide on IVF-level treatment, we fertilise every egg with ICSI. Conventional IVF is an older technique, and fertilisation outcomes are consistently better with ICSI.
That doesn't mean ICSI is automatically "right for everyone" everywhere. But at BFI, with our lab expertise and patient outcomes, ICSI has replaced conventional IVF as the standard. Here's why — and what the male partner's role looks like in an ICSI cycle.
Why we use ICSI, not conventional IVF
Conventional IVF places 50,000+ sperm around each egg and waits for one to fertilise it naturally. ICSI is different: our embryologist selects the single best sperm and injects it directly into each mature egg. Here is why we moved away from conventional IVF.
Conventional IVF vs ICSI
- Higher, more predictable fertilisation: ICSI gives 75–80% fertilisation per mature egg at BFI, versus 50–70% with conventional IVF — no 'total fertilisation failure' surprises.
- Removes binding uncertainty: even a 'normal' semen report can hide DNA fragmentation or egg-sperm interaction problems. ICSI bypasses that.
- Better across diagnoses: blocked tubes, endometriosis, PCOS, unexplained — fertilisation becomes one less variable to worry about.
- Matches modern standards: most top labs worldwide now do 80–90% ICSI.
Practical Tip
The male partner's role: it's 50% of the baby
ICSI makes sperm selection critical, which puts the male partner at the centre of the cycle — not on the sidelines. Here is what that role looks like, before and during treatment.
The Male Partner's Role
3 months before: build better sperm
- Advanced semen tests including DNA fragmentation (DFI). If DFI is high, three months of antioxidants can change outcomes.
- Lifestyle overhaul: sperm takes about 74 days to make — no smoking, no alcohol, no hot tubs, no tight underwear; add CoQ10, zinc and Vitamin E.
- Varicocele check by scrotal Doppler; if present, surgical correction before ICSI improves success.
Egg-retrieval day: your main medical role
- Give the sample after 2–5 days abstinence. If there's anxiety, we plan a backup — a frozen sample in advance.
- Zero-sperm cases: for azoospermia we do TESA, PESA or Micro-TESE the same day to retrieve sperm from the testis — our urologist is in-house.
- Best sperm picked: our embryologist uses IMSI and MACS to select sperm with the lowest DNA damage for injection.
Day 1 to the pregnancy test: your emotional role
Your partner will have 8–10 days of injections and scans — help manage appointments, medicines and mood swings. Then comes the two-week wait, where stress can affect implantation. Be the calm in the cycle: plan distractions, not Google searches.
IUI or ICSI? We diagnose first, then decide
We do not believe IUI is for everyone — or that IVF is. Whether you need IUI or IVF/ICSI at all depends on diagnosis. So we complete a full workup first: 3D ultrasound, AMH, HSG for the tubes and a hormone profile for her; semen analysis, DFI and Doppler for him.
IUI or ICSI — How We Decide
Why choose BFI for ICSI in Ahmedabad
- An ICSI-only lab: our entire workflow, quality control and embryologist training are optimised for ICSI — it's our baseline, not an add-on.
- Advanced sperm selection: IMSI at 6000x magnification, MACS for DNA-fragmented sperm, and microfluidics — we don't inject just any sperm.
- In-house male infertility unit: from varicocele surgery to Micro-TESE, no referrals needed.
- Transparent data and no blind protocols: we track fertilisation, blastocyst and live-birth rates, and still personalise your stimulation and transfer timing.
The BFI promise on ICSI
We use ICSI for every IVF patient because it gives higher, more predictable fertilisation — not because it's fancier.
The male partner is 50% of the baby — sperm health, sample day and steady support all matter.
We diagnose first. IUI, ICSI or neither is decided by your reports, never assumed.
Our whole lab is optimised for ICSI — IMSI, MACS and microfluidics select the best sperm.
Your time and emotional energy matter — we do what gives the highest chance, fastest.
Not sure if you need IVF, ICSI — or just IUI?
Come to Bavishi Fertility Institute for a complete fertility workup for both partners. We'll tell you honestly whether IUI can work, or if you need to move to ICSI — with a lab that has done 5,000+ ICSI cycles.
About the Author

Dr. Parth Bavishi
MBBS, MD (Obstetrics & Gynaecology)
Co-director & IVF Specialist
Dr. Parth Bavishi holds an MD in Obstetrics and Gynaecology and brings over 12 years of specialist experience as Co-director and IVF Specialist at Bavishi Fertility Institute — a group of fertility centres across India committed to helping couples realise their dream of parenthood. His clinical focus is on complex and challenging cases, including male-factor infertility, poor sperm quality, high sperm DNA fragmentation and repeated IVF failure. He has received specialised infertility training at Bavishi Fertility Institute, the Diamond Institute (USA) and the HART Institute (Japan), and is the author of 'Your Miracle in Making: A Couple's Guide to Pregnancy.'